
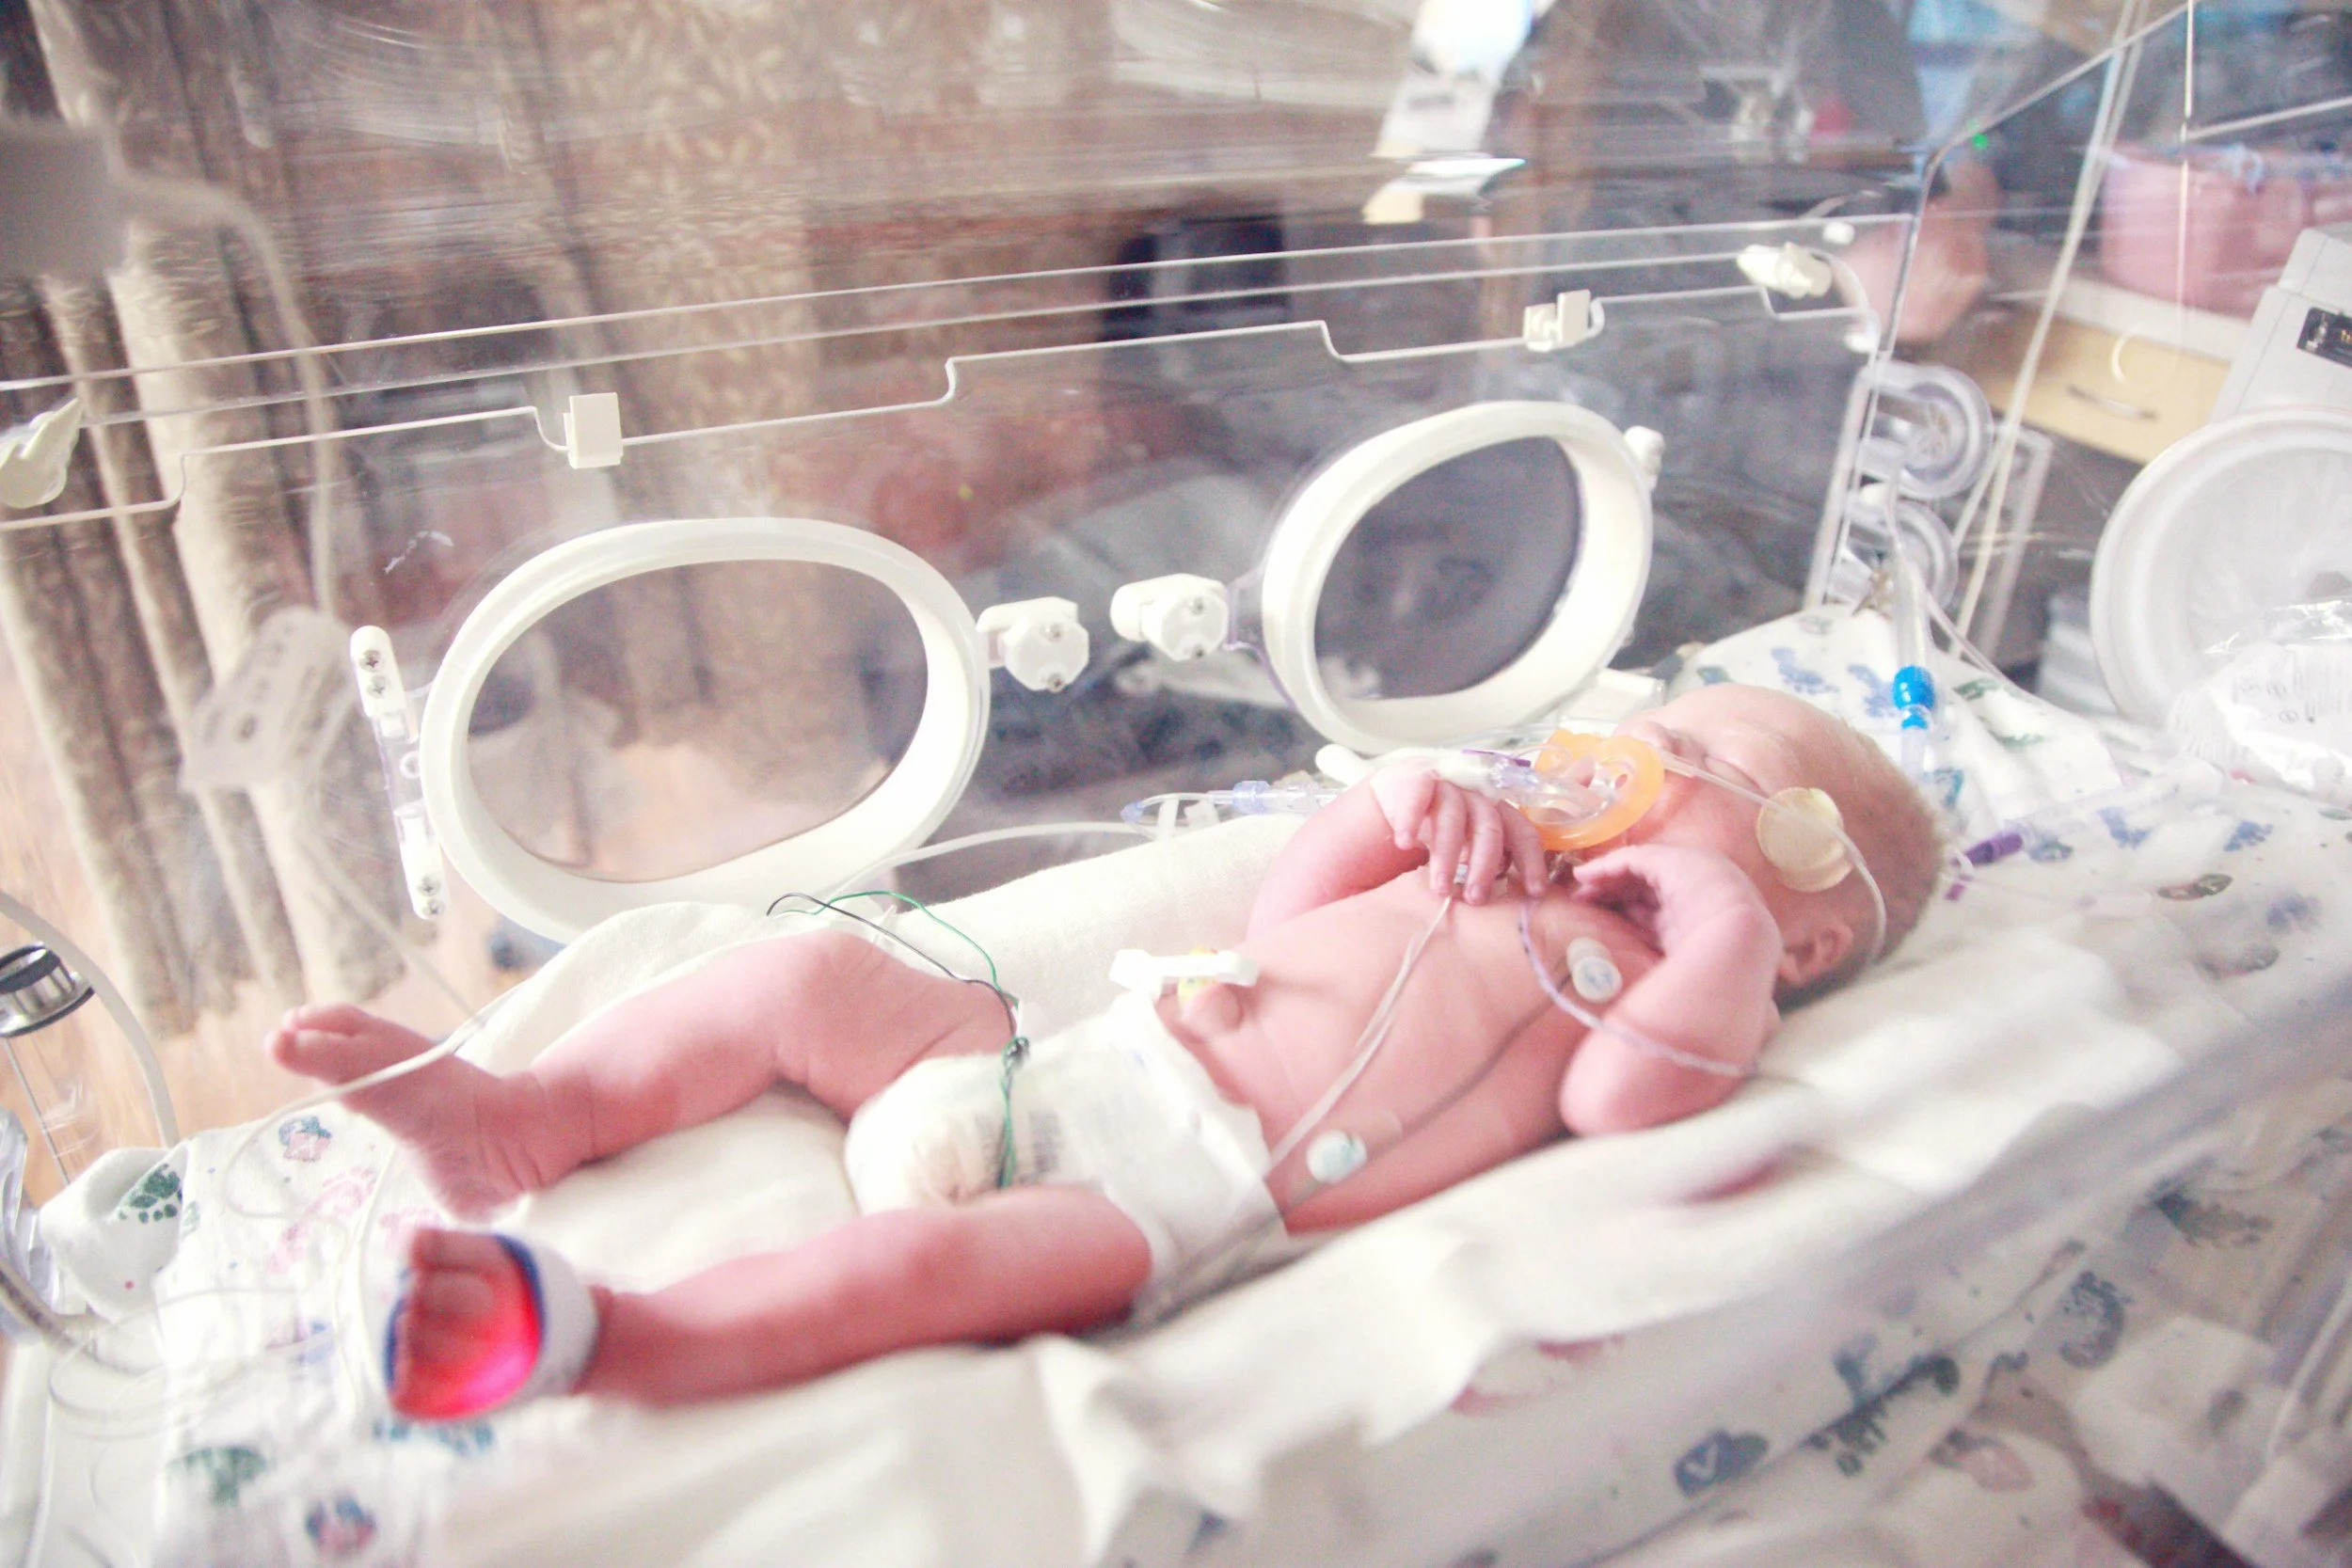
Recognizing Our Smallest And Most Vulnerable Patients
Recent federal healthcare decisions may place additional pressure on rural community hospitals already struggling to maintain maternity services.
By Marie Stinebuck, MBA, MSN, ACM
September was NICU Awareness Month, giving us time to recognize our smallest and most vulnerable patients, the professionals who care for them, and the families whose lives can change in an instant. This is also a topic I personally feel close to as the first 10 years of my nursing career were spent working in L&D and the neonatal ICU. My second child was also a NICU baby for the first month of his life.
Across the country, some communities have limited or no access to obstetric services and as the healthcare landscape continues to change and reimbursement decreases, the challenges for rural hospitals to provide maternal services becomes more challenging. When services are no longer offered in a rural community, a pregnant patient may need to travel a significant distance for routine prenatal visits, testing, maternal-fetal medicine appointments, or delivery. For someone with a high-risk pregnancy, that travel may be required more frequently.
Distance is more than an inconvenience. Each appointment may require reliable transportation, money for gas, time away from work, and childcare for other children. Weather, road conditions, or the inability to take unpaid time off may also affect whether a patient can keep an appointment.
When these barriers cause delayed or missed prenatal care, the healthcare team may have fewer opportunities to identify and manage complications early. Conditions such as high blood pressure, diabetes, abnormal fetal growth, or signs of preterm labor may become more difficult to monitor.
If the baby requires specialized neonatal care, the family’s challenges may increase significantly. The mother may deliver far from home, or the newborn may need to be transferred to another hospital with a higher level of NICU care. In some cases, the mother and infant become patients at different facilities while the mother continues to receive postpartum treatment.
Once the mother is discharged, the family must determine how to remain involved in the baby’s care. A NICU stay may last days, weeks, or even months. During that time, parents may be balancing transportation and hotel expenses, meals, employment responsibilities, childcare for siblings, and the ongoing cost of maintaining their household.
Recent federal healthcare decisions may place additional pressure on rural community hospitals already struggling to maintain maternity services. The 2025 federal budget reconciliation law reduces Medicaid funding over time through changes in enrollment and hospital payments. These changes could worsen access to rural maternity care by increasing financial pressure on hospitals, potentially contributing to additional service reductions or closures. For women and families, losing local maternity services can mean longer travel for delivery, greater transportation and childcare costs, and difficulty reaching care when complications arise. These challenges existed before the recent law; the concern is that funding reductions could deepen existing gaps in maternal care.
Distance can also affect the family’s preparation for discharge. Parents who cannot be at the bedside consistently may miss care conferences, feeding education, hands-on practice, or training related to medications and medical equipment. They may have fewer opportunities to build confidence in caring for a medically complex infant.
Case Management and Social Work should become involved as soon as a transfer or prolonged NICU stay appears likely. Families may need home-health services, medical equipment, medications, early-intervention services, and frequent specialty appointments. The plan should consider not only what the infant needs, but whether those services are available and accessible where the family lives.
NICU Awareness Month reminds us that caring for a newborn means caring for the entire family. When we identify barriers early, avoid judgment, and connect families with meaningful support, we help parents remain involved in their baby’s care and better prepared for the day they can finally go home together.

Celebrating the Moments Behind the Scenes
This profession is not for everyone. But for those of us who keep showing up, sometimes all it takes is one thank-you, one smile, or a moment of laughter over coffee with colleagues.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM, ACPA-C
This week, I want to recognize and celebrate the profession of case management. ACMA and the Commission have named this year’s theme “Driving Outcomes,” while CMSA calls us to “Reconnect, Recognize, Reignite, and Rise.” As I reflect on a field I have called home since 2009, I want to honor those who have committed themselves to serving people during their most vulnerable healthcare journeys, helping them find a path through a system that can feel both convoluted and overwhelming.
According to the CMSA Standards of Practice (2022), case managers are defined as healthcare professionals who serve as patient advocates to support, guide, and coordinate care for patients, families, and caregivers as they navigate their health and wellness journeys.
Our work may not be glamorous. It may be marked by heavy caseloads, needs for which no resource or easy solution exists, and moments when we must deliver difficult news. We are rarely the ones standing front and center; that space is often reserved for our physician and nurse colleagues. Yet the connections we make, the burdens we help carry, and the lives we touch are no less meaningful.
Thank you to my fellow case managers: for every hand you held when a patient could not imagine how they would leave the hospital; for every middle-of-the-night call you answered when the medical team needed you to return and help untangle a difficult social situation; for every set of clothes you found after the trauma team had cut theirs away. Thank you for the housing you secured, the bus tickets you provided, and the countless acts of charity care you approved, knowing full well that a patient had no way to pay for medications, rent, COBRA coverage, transportation, or the long-term care they desperately needed.
Thank you for helping travelers find their way home; for asking the nurse to check once more when something did not seem right; for every phone call you made to offer medical education and for the calls when the most important thing you offered was the grace to listen.
This profession is not for everyone. But for those of us who keep showing up, sometimes all it takes is one thank-you, one smile, or a moment of laughter over coffee with colleagues. Sometimes it is the shared glance after a story so improbable that all we can say is, “You could not make this up.” These are the moments that remind us why the work matters.
Today, this week, and in all the unseen moments still to come, I celebrate us and I celebrate you. Happy Case Management Week.

Understanding Medicare and Skilled Nursing Facility Placement
Understanding the differences between Traditional Medicare and Medicare Advantage is essential for Case Managers because insurance coverage can directly affect eligibility, authorization, network options, patient responsibility, and the timing of discharge.
By Marie Stinebuck, MBA, MSN, ACM
Navigating skilled nursing facility (SNF) placement can be complex, particularly when patients have different types of Medicare coverage. Understanding the differences between Traditional Medicare and Medicare Advantage is essential for Case Managers because insurance coverage can directly affect eligibility, authorization, network options, patient responsibility, and the timing of discharge.
Under Traditional Medicare, a patient generally must meet specific requirements for Medicare-covered SNF care, including a qualifying three-day inpatient hospital stay, available SNF benefit days, and a need for medically necessary skilled services. Importantly, time spent in the Emergency Department or under observation does not count toward the three-midnight requirement. The patient's hospital status therefore plays an important role in determining eligibility for SNF coverage.
The three-midnight rule requires three consecutive midnights in inpatient status. Simply spending three nights in the hospital does not satisfy the requirement if some of that time was spent under observation or another outpatient status. This makes accurate patient status determination an important component of the SNF discharge-planning process. The Utilization Review Nurse plays a vital role in validating appropriate inpatient status and helping identify potential barriers to Medicare-covered SNF placement.
Traditional Medicare generally does not require prior authorization for a Medicare-covered SNF admission once the patient meets the applicable coverage requirements. In contrast, Medicare Advantage plans commonly require prior authorization and may have additional network and plan-specific requirements. Case Managers must verify the patient's specific plan requirements early, including whether authorization is required, which SNFs are in network, what clinical information must be submitted, how many days may be authorized, and what the patient's financial responsibility will be.
Understanding patient financial responsibility is also important. Under Traditional Medicare, the first 20 SNF days are generally covered at $0 patient coinsurance after applicable Part A requirements are met. Beginning with day 21, patient coinsurance applies when the patient continues to meet skilled-care requirements. Medicare Advantage plans may have different cost-sharing structures and may authorize shorter periods of care, requiring additional reviews throughout the SNF stay.
A key responsibility of Case Management is to begin planning early rather than waiting until the patient is medically ready for discharge. When SNF placement becomes a likely discharge option, the Case Manager should verify insurance benefits, evaluate eligibility requirements, initiate referrals, identify network limitations, and begin authorization when required. Early planning can prevent avoidable delays and ensure that the patient and family understand potential barriers.
It is also important to recognize that a SNF recommendation does not automatically mean Medicare will cover the stay. The patient must meet the applicable coverage requirements, including the need for daily skilled services that are reasonable and necessary and can appropriately be provided in a SNF.
Finally, Case Managers should understand that the three-midnight rule is not absolute in every circumstance. Certain waivers and specific Medicare models may provide exceptions. Teams should therefore verify whether a waiver or other applicable exception exists rather than assuming that every patient must meet the standard three-midnight requirement.

Beyond “Inpatient” or “Observation”: Documenting the Why
Physician advisor notes don’t include treatment plans and aren’t written for bedside care, but they are still part of the record of decision-making.
By Juliet Ugarte Hopkins, MD, ACPA-C
Documentation in utilization review (UR) is practical daily work, but it carries significant operational, financial, and compliance weight. For physician advisors, especially those reviewing patient status, the documentation standard should be more than a one-word answer. A note that says only “inpatient,” “observation,” or “outpatient in a bed” may provide the utilization management team a recommendation, but it does not explain the clinical thinking behind it.
In medicine, the importance of documentation is taught early. Physicians, nurses, therapists, pharmacists, and many other professionals learn the familiar principle: if it was not documented, it did not happen. That same principle should apply when a clinician moves into the physician advisor role. Physician advisor notes don’t include treatment plans and aren’t written for bedside care, but they are still part of the record of decision-making. They should identify the case being reviewed, the clinical issue in question, and the rationale behind the status recommendation.
Too often, status escalations receive a brief response. A utilization manager requests a secondary review because the correct status is unclear, and the physician advisor responds, “inpatient.” Or, “observation.” The answer may be correct, but it leaves out the most important element: why. What about the patient’s presentation, severity of illness, intensity of service, treatment plan, risk of deterioration, comorbidities, or response to treatment supports the recommendation? What supported inpatient status? What made outpatient status with observation services more appropriate? Centers for Medicare & Medicaid Services (CMS) regulations recognize that inpatient status judgments depend on complex medical factors, including past medical history, comorbidities, severity of signs and symptoms, current medical needs, and risk of an adverse event. The factors supporting that expectation must be documented in the medical record.
The difference between a one-word recommendation and a brief rationale becomes clear when a denial arrives. If the physician advisor documented the reasoning at the time of review, the denial team can begin with that clinical thought process, rather than reconstructing the entire case weeks or months later. A concise note can frame a peer-to-peer discussion, support an appeal letter, and demonstrate that the status recommendation was tied to the patient’s condition and anticipated course at the time of hospitalization. It also helps separate contemporaneous clinical judgment from hindsight, which is especially important when the patient improves more quickly than expected.
Clear documentation is equally important during Recovery Audit Contractor (RAC) reviews and other governmental audits. An organization may discover that its physician advisors consistently supported inpatient status, but left no explanation of the medical necessity for a second midnight or the reasonableness of anticipating a two-midnight stay. In that situation, the organization may have had sound clinical judgment, but weak documentation of that judgment. The same concern applies to Condition Code 44 cases. When a Medicare beneficiary’s status is changed from inpatient to outpatient before discharge, they lose their right to appeal their discharge. In this instance as well, it’s important to identify the precise reasoning for the change in status.
Good physician advisor documentation also serves an educational purpose. Many secondary reviews are requested because the status decision is not obvious. A note that reads only “observation” does not help the next utilization manager recognize a similar clinical pattern. A brief explanation, however, can teach the logic behind the recommendation and improve consistency across future reviews. Over time, these notes become a practical teaching tool. They clarify how the organization applies regulatory guidance, payer expectations, and clinical judgment to real patients. They also help new utilization managers learn what details matter most when escalating a case for review.
If physician advisors report that they do not have time to document their rationale, leaders should evaluate the workload, rather than simply accepting shorter notes. It is important to count all secondary reviews, not only status cases. Peer-to-peer work, interdisciplinary rounds, huddles, meetings, denial support, and other daily responsibilities all compete for time. If the workload is too high to allow defensible documentation, the answer may not be less documentation, but rather additional physician advisor support, clearer escalation criteria, smarter workflows, or templates that make concise rationale easier to capture. The goal is not lengthy prose, but a short, clear explanation of the clinical judgment behind the recommendation.
Status recommendations need rationale. Clear documentation protects the organization, supports appeals, strengthens compliance, and helps the whole utilization review team learn from each case. In the end, a thoughtful physician advisor note is more than a status decision. It is a record of clinical judgment, a bridge between utilization management and medical necessity, and a safeguard for patients and organizations alike.

Have we figured out the Medicare Change of Status Notice (MCSN) yet?
The MCSN does not apply to every patient whose status changes from inpatient to outpatient, nor does it replace the MOON or the requirements associated with Condition Code 44.
By Sara Williams, RN, MSN, ACM
More than a year has passed since hospitals were required to implement the Medicare Change of Status Notice (MCSN), yet the notice remains a source of operational confusion. Some organizations have struggled to reliably identify which beneficiaries qualify for the notice, while others have attempted to incorporate the MCSN into existing Medicare Outpatient Observation Notice (MOON) or Condition Code 44 workflows without fully accounting for the differences among these requirements.
The challenge is understandable. The MCSN does not apply to every patient whose status changes from inpatient to outpatient, nor does it replace the MOON or the requirements associated with Condition Code 44. Instead, it creates additional beneficiary protection for a specific population of Traditional Medicare beneficiaries whose status is changed from inpatient to outpatient receiving observation services.
Consider Mr. Smith, a Traditional Medicare beneficiary with Medicare Parts A and B. He is formally admitted as an inpatient following a ground-level fall and remains hospitalized for several days. During the hospitalization, Utilization Review identifies that inpatient criteria was not supported and refers the case for Condition Code 44. Following review, the hospital reclassifies Mr. Smith from inpatient to outpatient receiving observation services while he is still hospitalized.
Because Mr. Smith has Medicare Part B and his hospital stay lasted at least three days, he now meets the requirements for the expedited status appeal process, via the MCSN. However, his case management team has forgotten about the notice, and instead are working on alternative discharge plans with Mr. Smith as he prolongs his observation stay in the hospital. In this instance, Mr. Smith, had he received the MCSN, may have elected to appeal to the BFCC- QIO with an opportunity for inpatient from time of the initial inpatient order granting his 3 midnights and SNF eligibility.
Why Is the MCSN So Difficult to Operationalize?
Much of the confusion stems from two factors: not every Medicare beneficiary who experiences an inpatient-to-outpatient status change is eligible for the MCSN, and the timing of notice delivery varies based on Medicare Part B coverage. These nuances make MCSN compliance more complex than simply identifying that a patient's status changed from inpatient to outpatient with observation services.
How Did We Get Here?
The MCSN originated from a 2011 class-action lawsuit that challenged Medicare’s failure to provide appeal rights for patients reclassified from inpatient to observation status. These changes created significant financial consequences, especially when beneficiaries later required SNF care but lacked the qualifying inpatient hospital stay needed for Medicare coverage.
The litigation and subsequent CMS actions resulted in an appeal process for certain Traditional Medicare beneficiaries whose status is changed from inpatient to outpatient while receiving observation services. The MCSN is the mechanism used to notify eligible beneficiaries of these appeal rights.
While the concept sounds straightforward, the operational requirements are not.
Who Should Receive the MCSN?
To qualify, the beneficiary must have been formally admitted as an inpatient and subsequently reclassified as an outpatient receiving observation services, remain physically present in the hospital when the reclassification occurs, and meet applicable eligibility and timing requirements.
The timing requirement presents one of the greatest operational challenges because Medicare Part B entitlement affects when the notice must be delivered.
For beneficiaries without Medicare Part B, the MCSN should be delivered as soon as possible following the decision to reclassify the patient. For beneficiaries with Medicare Part B, notice requirements are tied to the applicable three-day hospital stay requirement. Hospitals must therefore track the beneficiary's stay and determine when the patient reaches three days from the original inpatient order.
A hospital cannot simply build an electronic rule stating, "Inpatient changed to observation = MCSN." Instead, the workflow must consider Traditional Medicare versus Medicare Advantage, Part B entitlement, initial inpatient status, subsequent status change, continued physical presence in the hospital, length of stay, and anticipated discharge. Without these elements incorporated into the workflow, hospitals risk both failing to issue required notices and issuing notices to beneficiaries who do not meet the requirements.
MCSN, MOON, and Condition Code 44 Are Not Interchangeable
Another source of confusion is the relationship between the Medicare Change of Status Notice (MCSN), Medicare Outpatient Observation Notice (MOON), and Condition Code 44. Although all three may intersect during a hospitalization, they serve different purposes.
The MCSN advises an eligible Traditional Medicare beneficiary of the right to appeal a qualifying change from inpatient to outpatient status while receiving observation services. The MOON informs Medicare beneficiaries receiving observation services that they are hospital outpatients rather than inpatients and explains the implications of outpatient status. Condition Code 44 relates to the process through which an inpatient admission is changed to outpatient status for Traditional Medicare patients when applicable Medicare requirements are satisfied. Hospitals should not assume that an existing MOON or Condition Code 44 workflow automatically satisfies MCSN requirements.
What Happens if the Patient Appeals?
The MCSN provides eligible beneficiaries access to an expedited determination by the BFCC-QIO. Importantly, the beneficiary is challenging the decision to change the hospitalization from inpatient to outpatient status, not simply appealing discharge or requesting a conversion back to inpatient. UR, Physician Advisors, Case Management, Patient Access, Revenue Cycle, Health Information Management, and other involved departments must understand this distinction and their responsibilities when an appeal occurs.
Hospitals must also establish a process for beneficiaries who remain hospitalized while the QIO reviews the appeal. Because continued services may result in financial liability, organizations need clear procedures for communicating potential financial responsibility and determining when an Advance Beneficiary Notice of Noncoverage (ABN) is appropriate.
Building a Reliable Hospital Workflow
A strong MCSN process begins with automated identification whenever possible. Reliance on staff memory or manual review creates unnecessary compliance risk because eligibility depends on multiple data elements that may reside in different systems.
Ideally, the EHR should identify potential MCSN cases and evaluate Medicare coverage, Part B enrollment, length of stay, continued hospitalization, and timing of the status change. Once eligibility is established, an actionable alert should be generated for the department responsible for notice delivery. Organizations should also clearly define who delivers the notice, how delivery is documented, who manages an appeal, and how communication occurs across clinical and revenue cycle teams.
More Than a Year Later: The Opportunity for Hospitals
More than a year after implementation, hospitals should be asking:
Are we reliably identifying every beneficiary eligible for the MCSN?
Are we avoiding delivery to beneficiaries who do not meet the requirements?
Can we demonstrate that the notice was delivered appropriately?
If a beneficiary appeals tomorrow, does everyone involved know what happens next?
The organizations that manage this requirement most successfully will move away from manual processes and isolated departmental ownership toward a standardized, technology-supported workflow. The goal is simple but critical: identify the right patient, deliver the right notice at the right time, protect the beneficiary's appeal rights, and ensure the hospital is prepared when those rights are exercised.

What’s In a Name: Is it UR or UM?
There is an important distinction between the two, and that distinction may be becoming more important as healthcare moves further away from managing individual encounters towards managing total utilization and episodes of care.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
Ask a group of hospital leaders whether their organization has a Utilization Review (UR) or a Utilization Management (UM) department, and the answers will likely vary. In many organizations, the terms are used interchangeably. Job titles may include UR nurse, UM specialist, UM director; you get the point. This occurs even when the individuals are performing essentially the same work.
But are UR and UM actually the same? There is an important distinction between the two, and that distinction may be becoming more important as healthcare moves further away from managing individual encounters towards managing total utilization and episodes of care.
At its most basic level I have always considered utilization review as micro practice, while utilization management as macro practice. What I mean is, utilization review focuses primarily on the individual patient encounter. Does this patient require inpatient hospitalization? Does the documentation support the level of care? Does the case require escalation to a physician advisor? Has the payer authorized the services being provided?
The term ‘utilization review’ also has a specific regulatory foundation. Medicare’s Conditions of Participation at 42 CFR §482.30 require hospitals to maintain a utilization review plan addressing the medical necessity of admissions, duration of stays, and professional services furnished. Yet like all things from the time of 482.30 being written, we have naturally evolved beyond the term utilization review, into the management arena.
Traditional UR has largely been built around the hospital encounter. A patient arrives in the emergency department, a decision is made regarding hospitalization, and UR evaluates whether the patient meets the requirements for inpatient or outpatient care, often with observation services. Concurrent review then follows the patient through hospitalization. That model made sense when the hospital encounter was largely evaluated and reimbursed as an individual event. Increasingly, however, hospitals are operating in an environment where the financial and clinical consequences of utilization extend well beyond a single admission or even payer demands.
Consider an uninsured patient. There may be no payer authorization to obtain and no insurance company requesting concurrent clinical reviews. Under our old model, we may ignore this case, but from a utilization management perspective, this case is total financial risk to the organization.
The same evolution can be seen in CMS payment models. Models such as CJR-X will reinforce the importance of looking beyond the walls of the hospital and considering utilization across an episode of care. When organizations assume greater accountability for the cost and outcomes associated with an episode, utilization decisions cannot be isolated to whether the initial hospital admission met criteria. This is going to push the UR to UM model as we are evaluating length of stay, post-acute utilization, readmissions, avoidable emergency department use, and patient progression.
While UR can help to determine whether the individual service was appropriate. Maybe now it is the UM professional who asks whether the entire pattern of care was appropriate. Thus, an adaptive UM program requires data, physician engagement, case management, revenue cycle, CDI, finance, nursing, operational leadership, and utilization professionals working from a shared strategy.

How to Ensure Collaboration Between UM, Clinicians When Considering Status
I have long supported educating medical staff on medical necessity, the Two-Midnight Rule, and the practical application of the Rule to all patients.
By Juliet Ugarte Hopkins, MD, ACPA-C
More than a decade after its October 2013 implementation, the Medicare Two-Midnight Rule should, in theory, be one of the simplest and most straightforward frameworks for assigning hospital status. In practice, however, it remains a persistent source of confusion for hospitals, clinicians, utilization managers, and even payers themselves.
Some Medicaid status determinations are also based on the Two-Midnight Rule, but this is not universal from state to state. Additionally, some states have other qualifiers for Inpatient status, which can be confounding from a medical necessity perspective because they may rely more on the length of hospitalization than on the true need for hospital services.
Commercial plans often align themselves with one of the two major criteria-set guidelines, and while these guidelines promote themselves as grounded in evidence-based practice, there is no way to care for patients as if following along in a cookbook.
Finally, status assignment associated with Medicare Advantage plans may be the most confounding of all, given their assigned obligation, per the Centers for Medicare and Medicaid Services (CMS), to utilize the Two-Midnight Rule, coupled with a lack of obligation to trust the attending clinician’s determination of medical necessity for continued hospital care.
Taking all of this into account, it makes sense that utilization managers have long served as an important resource for clinicians when deciding appropriate patient status. Whether at the time of hospitalization or a day or two later, physician advisors and utilization management leaders routinely emphasize to their hospitals’ medical staffs that clinicians should actively collaborate with, and rely on, utilization managers to assist with appropriate statusing of their patients.
What is not standard? The clinicians involved in these conversations about patient status, how the communication takes place, and how the decided-upon status order is entered into the electronic medical record. These variations from hospital to hospital may be justifiable, but at the end of the day, all must comply with CMS rules, in particular 42 CFR § 412.3 from the Code of Federal Regulations.
As I reviewed in an article in February of this year, the Rule explicitly states, “The expectation of the physician should be based on such complex medical factors as patient history and comorbidities, the severity of signs and symptoms, current medical needs, and the risk of an adverse event…” and, “…who is…knowledgeable about the patient’s hospital course, medical plan of care, and current condition at the time of admission.”
Do emergency medicine physicians meet this qualification when they decide a patient must be hospitalized and is not appropriate for discharge from the emergency department (ED)? I say no, since their scope of the patient’s care involves only the time spent in the ED. They are not considering the future hospital course or medical plan of care following the patient’s departure from the ED.
As such, I do not believe they can compliantly designate a Medicare patient as Inpatient or Outpatient with Observation services. However, standard operating procedure in many hospitals involves ED utilization managers working side by side with ED physicians and providing, among other things, suggestions on appropriate patient status.
Relatedly, even if the suggestions are not directed to the ED physicians but instead to the accepting or attending physicians, the practice can be just as problematic. There is an important distinction between collaborating with a physician to come to agreement on appropriate status assignment and dictating status assignment. Unfortunately, this is a scenario I am hearing about increasingly often. The utilization nurse manager, applying MCG or InterQual criteria or using their own clinical judgment to suspect that an at least two-midnight hospitalization will be required, communicates to the attending physician what status should be chosen. There is no discussion, no sharing of the points the utilization manager is considering to make the determination, just direction of Inpatient or “Observation.” Then, either the clinician places the order as directed, or, in even more egregious situations, the order has already been placed as pended in the electronic health record by the utilization manager and only needs the physician’s signature to complete and activate.
The common reasoning for this practice is that utilization managers are experts in patient statusing and are the best and most readily available resource for clinicians making this decision. I do not disagree with that. However, in virtually all the scenarios I have encountered across the country, the main reason is to take responsibility out of the clinicians’ purview entirely, with the aim of avoiding inappropriate status determinations.
In effect: do not bother teaching clinicians how to status patients; just tell them to order whatever status the utilization manager tells them to pick.
I believe this is a non-compliant practice and that it runs counter to 42 CFR § 412.3. In this instance, the clinician is not taking into account the factors the Rule requires to make the status determination. All they do is accept direction from the utilization manager and affix their signature to it.
How do I know this? Because when I ask clinicians working within hospitals that use this practice how they determine status for their patients, they tell me, “I have no idea; I just pick whatever the utilization manager tells me to pick.” This cannot be your medical staff’s answer. In the event of an audit, in theory, it could lead to a devastating retrospective review of months and months of Inpatient cases.
So what should hospitals do instead? I have long supported educating medical staff on medical necessity, the Two-Midnight Rule, and the practical application of the Rule to all patients. True, some of their decisions will be incorrect in cases involving commercial or even some Medicaid plans, but at least they will be following the direction of 42 CFR § 412.3 for the Medicare population. After that is when utilization managers come into play, reaching out with corrections when needed because a payor does not follow the Rule.
In real time, can utilization managers help clinicians make status determinations? Absolutely. But the key word is help. This interaction should be a discussion about the patient’s condition, the plan of care, and the medical factors supporting the conclusion. Utilization managers should be trusted collaborators and expert resources, not substitutes for the clinician’s required judgment.
The goal is not to remove clinicians from status assignment; it is to make sure they are prepared to make, understand, and own the determination in a way that is clinically sound and compliant.

When a Hospice Patient Comes to the Hospital
A hospital presentation does not automatically terminate the hospice election.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
A recent question was posed related to “What happens when a hospice enrolled patient returns to the hospital for emergency or hospital care?”
Aside from the initial questions such as “did we even know this patient was on hospice when they roll through the emergency room, or why did they come back to the hospital? The next question may evolve to the following: is the treatment still involving care congruent with the patient’s hospice care plan or has the patient/representative elected to revoke their hospice services?“
Understanding these distinctions is increasingly important for case management, utilization review, registration, revenue cycle, and especially hospital clinical teams. Particularly with the publication here last week of my article on Advance Care Planning.
The Medicare rules are more specific than many hospital workflows suggest. For reference, under the Centers for Medicare & Medicaid Services (CMS) requirements, an individual must be entitled to Medicare Part A and certified as terminally ill to elect the Medicare hospice benefit.
CMS defines terminal illness as a medical prognosis that the individual’s life expectancy is six months or less if the illness runs its normal course. The beneficiary or authorized representative must then elect hospice with a particular Medicare-certified hospice agency.
During a hospice election, CMS states that the beneficiary waives Medicare payment for services related to treatment of the terminal illness and related conditions, with limited exceptions. Those services remain covered when they are furnished by the following:
The designated hospice, either directly or under arrangement;
Another hospice under arrangements made by the designated hospice; or
The beneficiary’s designated attending physician, subject to CMS requirements.
The patient’s hospice election remains in effect until it is terminated through an allowable process, such as revocation or discharge from hospice. Therefore, when a hospice patient arrives at a hospital for a condition potentially related to the terminal illness, communication with the designated hospice is important for determining the patient’s status with their hospice services, the treatment plan, and who is financially responsible for the hospitalization.
Services for conditions completely unrelated to the terminal illness and related conditions can remain covered under Medicare. CMS, however, advises that this should be rare and unusual.
Revoking Hospice
If the patient is receiving services related to their treatment, typically a change in the goals of care back to aggressive treatment, this would require formal hospice revocation. CMS states that an individual or authorized representative may revoke hospice at any time. However, the hospice itself cannot revoke the beneficiary’s election. Revocation must be made in writing. The beneficiary must file a document with the hospice that includes a signed statement revoking their hospice election and the effective date of this revocation. CMS states that this cannot be made verbally or retroactive, and it must come from the patient and/or representative, not the hospice agency.
Once hospice is revoked, the beneficiary is no longer covered under the Medicare hospice benefit for the remainder of that election period and resumes Medicare coverage of the benefits that had been waived through the hospice election. Consider a beneficiary who remains enrolled in hospice when admitted to the hospital on Aug. 8 and subsequently signs a hospice revocation effective Aug. 10.
The revocation cannot be made retroactive to Aug. 8. This demonstrates why the hospital should have this form on file, when billing occurs. As the hospital would bill the hospice for Aug. 8 and 9 services, while starting Aug. 10, Medicare Part A would assume financial responsibility.
There is an additional layer when the beneficiary is enrolled in a Medicare Advantage plan. During the hospice election, coverage for hospice-related services reverts to Traditional Medicare. According to CMS guidelines, if a Medicare Advantage beneficiary revokes hospice or is discharged alive, Traditional Medicare continues to provide coverage through the end of that calendar month.
Medicare Advantage coverage resumes on the first day of the following month.
An Example: Hospice Revocation
Hospice revocation is effective Monday, Aug. 10, from the ED and time of admission. The patient is discharged home on Tuesday, Aug. 18. Traditional Medicare remains responsible for Medicare coverage through August 31. Medicare Advantage billing and coverage resumes Sept. 1.
In summary, the central concept is that hospice is an election of a Medicare benefit. During the hospice election, the beneficiary waives Medicare payment for services related to the terminal illness and related conditions, except as permitted under the hospice benefit. A hospital presentation does not automatically terminate the hospice election.
Revocation requires written action by the beneficiary or authorized representative. It cannot be initiated by the hospice or applied retroactively.
For Medicare Advantage beneficiaries, the transition following hospice revocation requires additional consideration. Traditional Medicare coverage continues through the end of the calendar month in which hospice is revoked. Medicare Advantage coverage resumes on the first day of the following month. Understanding these requirements helps hospitals identify the appropriate payer, coordinate services with the hospice agency, and apply Medicare requirements correctly when hospice-enrolled patients require hospital care.

When Advance Care Planning Becomes a Hospital Quality Measure
Existing advance care planning documentation already available within the patient’s EMR satisfies the measure, provided it remains accessible during the admission.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
The Centers for Medicare & Medicaid Services (CMS) finalized adoption of the Advance Care Planning electronic Clinical Quality Measure (eCQM) as a new self-selected electronic quality measure in the FY 2027 finalized Inpatient Prospective Payment System (IPPS) ruling.
This additional quality metric is expected to start voluntarily CY 2028 and will be mandatory in calendar year (CY) 2029 reporting period for the fiscal year (F) 2031 payment determination under both the Hospital Inpatient Quality Reporting (IQR) Program and the Medicare Promoting Interoperability Program.
This measure was very clear on going beyond asking the question, “Do you have an Advance Directive?” Instead, CMS intentionally designed the measure to recognize multiple ways hospitals can demonstrate meaningful advance care planning either by verifying appropriate documents exist in the medical record or clear documentation exists to support this measure.
A patient meets the numerator if any one of the following exists by hospital discharge from an inpatient encounter:
A documented health care proxy or medical power of attorney
An advance directive or living will
A POLST, MOLST, or qualifying DNR order
Documentation of an advance care planning discussion that resulted in a documented decision in the electronic medical record (EMR)
Importantly, the measure does not require a new document to be completed during every hospitalization. Existing advance care planning documentation already available within the patient’s EMR satisfies the measure, provided it remains accessible during the admission. CMS intentionally declined recommendations to require hospitals to create or revise documentation on every encounter, recognizing that doing so would increase burden without necessarily improving patient care.
Another notable aspect of the final rule is the broad denominator. The measure applies to all inpatient hospitalized adults aged 18 years and older, regardless of diagnosis, severity of illness, or length of stay. CMS specifically rejected recommendations to limit the measure to oncology patients, older adults, ICU patients, or patients with extended hospitalizations.
CMS emphasized in the final rule comments that serious illness, unexpected injury, and loss of decision-making capacity can occur at any age, making advance care planning relevant for every adult patient admitted to an acute care hospital. For hospitals accustomed to focusing advance directive discussions primarily on older adults or palliative care populations, this represents a substantial workflow expansion.
Interestingly enough in the comments there was also discussion from the public raising concern that this measure would inadvertently force uncomfortable end-of-life discussions during acute hospitalizations. I thought that was interesting from a case manager and social work perspective, as we often do encounter providers who are uncomfortable asking these questions to patients and/or their families because of their own moral distress and uncomfortableness with this topic.
What I would expected to see was more comments related to the time it takes for these conversations or that the inpatient setting when crisis occurs is often not the best time to have this discussion, however from the CMS opening statement that the advance care planning incentive in the outpatient setting, is frankly not working.
CMS responded that this is not about end of life, but about documenting patient preferences, identifying surrogate decision-makers, and ensuring clinicians have access to information necessary to provide goal-concordant care across settings. CMS also noted that hospitalization often provides an important opportunity to confirm existing wishes or initiate conversations for patients who may not routinely receive primary care.
Equally important, hospitals are not penalized when patients decline to complete an advance directive or designate a health care proxy. Documentation that an advance care planning conversation occurred, even when the patient chooses not to make decisions or wishes to defer the conversation, will still satisfy the numerator requirements if documented appropriately.
Now is a good time to begin collaborating with quality, nursing, case management/social work, palliative care, medical staff, registration, chaplaincy, and IT teams to assess current compliance and identify opportunities to standardize documentation in discrete medical record fields for data collection.
Establishing baseline data now will help healthcare organizations determine how to operationalize this metric and related processes moving forward.

Proposed Increased Home Health Oversight Generates Questions
Hospitals continue to experience limited post-acute capacity with delayed transitions of care, while simultaneously caring for an aging population whose demand for home-based services continues to grow.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
Typically, each year, the Centers for Medicare & Medicaid Services (CMS) Home Health Prospective Payment System (HH PPS) proposed rule brings expected discussions around payment updates, wage indexes, and Patient-Driven Groupings Model (PDGM) refinements.
While those financial provisions continued to remain important in the proposed rule, another topic area of program integrity and provider accountability really continued to be the center stage in this proposal.
Putting this in the context with the U.S. Department of Health and Human Services (HHS) Office of Inspector General (OIG) 2025 audit, with a very little sample size, reported a big financial opportunity of $1.2 billion. Fast forward to May of this year, and CMS announces a six-month nationwide moratorium on new Medicare enrollment for home health agencies and hospices, along with intensified investigations, advanced data analytics, and faster removal of providers suspected of fraud.
The CY 2027 proposal serves as another reminder that documentation, enrollment compliance, and clinical decision-making remain under increased scrutiny.
CMS is proposing several changes designed to strengthen its ability to identify non-compliant providers and recover improper payments. Among the most notable proposals are the following:
Retroactive application of all Medicare enrollment revocations, allowing CMS to recover payments back to the date noncompliance began rather than only prospectively.
New denial and revocation authorities related to changes in majority ownership for home health agencies that fail to comply with required reenrollment and survey requirements.
Expanded authority to deny or revoke enrollment when owners, managing employees, or managing organizations have experienced licensure suspensions or exclusions from Medicaid or other federal healthcare programs.
From the acute care perspective, these proposals have implications well beyond the home health industry itself. Hospitals continue to experience limited post-acute capacity with delayed transitions of care, while simultaneously caring for an aging population whose demand for home-based services continues to grow. Case management teams have increasingly relied on home health as a critical component of safe transitions from hospital to home, recognizing its role in reducing avoidable readmissions.
However, increased regulatory oversight may create additional challenges for agencies already operating on narrow financial margins. While there is little debate that fraud and abuse must be addressed, many of the payment suspensions and recoupments currently identified seem to be more associated with insufficient documentation supporting Medicare coverage requirements. These appear to include the following:
Failure to adequately support homebound status;
Insufficient documentation demonstrating medical necessity for skilled services;
Incomplete or delayed physician certifications and plans of care; and
Lack of documentation showing continued skilled need throughout the episode of care.
As enforcement activities are expected to continue, documentation quality becomes increasingly important. The referral process, certification, and initiation of home health services will need to demonstrate medical need that the patient qualifies as homebound, that the ordered skilled services are medically necessary and aligned with the patient’s clinical condition, and that the care plan has measurable clinical goals. Additionally, there must be clear involvement from the physician/provider throughout the episode of care with appropriate reassessment of ongoing skilled need.
For reference CMS defines homebound as home health services are or were required because the individual is or was confined to the home per the criteria below (as defined in sections 1835(a) and 1814(a) of the Social Security Act).
Criteria-One: The patient must – Because of illness or injury, need the aid of supportive devices such as crutches, canes, wheelchairs, and walkers; the use of special transportation; or the assistance of another person in order to leave their place of residence OR – Have a condition such that leaving his or her home is medically contraindicated. If the patient meets one of the Criteria-One conditions, then the patient must ALSO meet two additional requirements defined in Criteria-Two below.
Criteria-Two: – AND – There must exist a normal inability to leave home; Leaving home must require a considerable and taxing effort. In determining whether the patient meets criterion two of the homebound definition, the clinician needs to take into account the illness or injury for which the patient met criterion one and consider the illness or injury in the context of the patient’s overall condition.
For hospitals and healthcare organizations, this proposed rule serves as an important reminder that compliance does not begin when the home health agency admits the patient but rather during the discharge planning process. Case management teams should ensure referrals demonstrate the medical necessity requirements for homebound status, skilled need, physician involvement, and clearly defined goals of care. Likewise, healthcare organizations should consider evaluating their own transition-of-care processes and partnerships with home health agencies to identify potential compliance risks before they result in payment denials or delays in patient care.
It may be time for a good refresher with case management (CM), physician advisors, and high-volume referring providers such as hospitalists, to understand the requirements for home health services. Particularly going beyond the requirements for patient choice and discharge disposition documentation of ‘home with home health’.
If you are a healthcare organization that also has its own home health division, an internal audit is likely a good idea at this time. Finally, this is also a great opportunity to strengthen partnerships between hospitals and their preferred home health providers.
Regular meetings to review denial trends, documentation deficiencies, referral turnaround times, and regulatory updates can improve both compliance and patient outcomes.
As more home health agencies operate under increased regulatory scrutiny, they will likely become more selective in accepting referrals that lack sufficient documentation or present elevated compliance risk; straining patient home-based care options.

The IPO List Continues to Disappear
As this list disappears, hospitals are losing a regulatory shortcut, and must instead rely on physician documentation and strong utilization management processes to support level-of-care decisions.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
The 2027 Outpatient Prospective Payment System (OPPS) Proposed Rule has listed the intent to remove an additional 637 procedures from the Inpatient-Only (IPO) List as the second phase of its three-year elimination strategy. The Centers for Medicare & Medicaid Services (CMS) stated several times in the ruling that they are leaving only the most clinically complex services for removal in 2028.
If finalized, nearly half of the remaining IPO List procedures will become eligible for either inpatient or outpatient payment, based on medical necessity, rather than a predetermined designation. The proposal includes procedures across multiple clinical families, including digestive, respiratory, urinary, endocrine, maternity, male and female genital, mediastinum and diaphragm, hemic and lymphatic systems, and auditory services. CMS intentionally delayed removal of neurological procedures, cardiovascular procedures, and transplant-related services until 2028, acknowledging their greater clinical complexity and the need for additional evaluation of appropriate Ambulatory Payment Classification (APC) assignments.
CMS explained that the procedures proposed for removal generally require fewer modifications to the existing APC structure than the more complex procedures planned for 2028. According to CMS, many of the services proposed for removal already have clinical characteristics and resource utilization similar to procedures currently paid under the OPPS. In contrast, CMS noted that neurological, cardiovascular, transplant, and other highly specialized procedures will require additional review because of their greater clinical complexity, and may necessitate revisions to existing APC or Comprehensive APC (C-APC) payment methodologies before they can appropriately transition to outpatient payment.
CMS reiterated in the ruling its policy that once a procedure is removed from the IPO List, it becomes eligible for payment in either the inpatient or hospital outpatient setting. The appropriate setting continues to depend on whether the service is reasonable and necessary, based on the individual patient’s clinical circumstances and existing Medicare coverage policies. Thus, while the procedure itself may no longer auto classify as an inpatient admission, physicians must continue to determine the appropriate level of care based on the patient’s overall condition, expected hospital stay, comorbidities, procedural risk, and anticipated postoperative care needs.
For decades, the IPO List served as a safety net. Certain procedures were automatically considered inpatient, eliminating much of the clinical debate surrounding admission status. As this list disappears, hospitals are losing a regulatory shortcut, and must instead rely on physician documentation and strong utilization management processes to support level-of-care decisions.

Factors Supporting Inpatient Status for Medicare Patients Undergoing Non-Inpatient-Only Procedures
This policy change creates a need for careful, patient-specific status determinations, rather than automatic assumptions based only on the procedure being performed.
By Juliet Ugarte Hopkins, MD, ACPA-C
Jan. 1, 2026 marked the start of the Centers for Medicare & Medicaid Services (CMS) plan to end the Medicare Inpatient Only List.
Most musculoskeletal procedures were removed first, with the entire list expected to be eliminated as of Jan. 1, 2028. This policy change creates a need for careful, patient-specific status determinations, rather than automatic assumptions based only on the procedure being performed.
As in 2018, when total knee arthroplasty was removed from the list, removal of a procedure does not mean that every such procedure must be classified as outpatient. Instead, the clinical team must evaluate the individual patient’s medical condition, functional needs, home situation, and anticipated post-operative course.
The points below should guide decisions to place a patient into inpatient status when the surgeon or treating clinician reasonably anticipates that the patient will require at least two midnights of hospitalization during recovery before being safe for discharge on post-operative day two or later.
Patient Factors That May Support Inpatient Status
If the patient has any of the following conditions or needs, inpatient hospitalization may be appropriate when the reason is clearly documented in the medical record.
An expectation that the patient will require transfer to a Skilled Nursing Facility (SNF) after surgery for skilled care supports inpatient hospitalization when the documentation explains why skilled care in a facility will be needed, and why discharge home with home services will not be appropriate after surgery. Examples include the absence of family or friends to assist at home, multiple stairs, or other unmanageable obstacles within the home environment. CMS anticipates that these patients will not be ready for hospital discharge until post-operative day three, which allows them to use their Medicare SNF benefit for covered charges when all requirements are met. However, the clinician still must document what services the patient is receiving while hospitalized, why the patient cannot safely discharge home, and what medical needs require a SNF setting, on a daily basis. SNF transfer for custodial needs alone will not be covered by Medicare.
A body mass index (BMI) of 40 or greater may support inpatient hospitalization. Documentation should include the patient’s increased surgical and anesthesia risk due to elevated BMI and the need for careful post-operative monitoring.
Poorly controlled diabetes mellitus with a HbA1C greater than 7.5 percent may support inpatient hospitalization. Documentation should include the increased risk of post-operative hyperglycemia and wound infection.
Chronic anemia with a baseline hemoglobin under 11 may support inpatient hospitalization. Documentation should include the need for careful attention to blood loss and post-operative monitoring for signs and symptoms that could require transfusion.
Chronic Kidney Disease Stage 4 or 5 (CKD IV or CKD V) may support inpatient hospitalization. Documentation should include the increased risk associated with anesthesia administration and the need for increased post-operative monitoring of fluid balance and possible development of acute kidney injury.
Coronary Artery Disease (CAD) treated with chronic medication may support inpatient hospitalization. Documentation should include the increased surgical risk and the need for close post-operative monitoring.
Uncontrolled hypertension while on medication therapy, such as blood pressure over 140/90 in previous documentation, may support inpatient hospitalization. Documentation should include the increased risk of surgery and increased risk of bleeding that requires close post-operative monitoring.
Chronic Obstructive Pulmonary Disease (COPD) treated with regularly scheduled oral or inhaled medications may support inpatient hospitalization. Documentation should include the increased risk of perioperative respiratory failure and other respiratory complications.
A baseline abnormal mental status may support inpatient hospitalization. Documentation should include the need for careful post-operative monitoring of mental status after anesthesia and while the post-operative pain management regimen is established and tailored for the patient.
Procedure-Related Factors That May Support Inpatient Status
In addition to patient-specific medical and functional risks, the anticipated complexity of the procedure and the expected post-operative course should be considered before assigning status:
If the procedure is expected to be technically challenging or difficult because of anatomical factors unique to the patient, hospitalize the patient as inpatient and document the reasons in detail.
If the patient is expected to require at least two midnights of post-operative care that can only take place in the hospital, hospitalize the patient as inpatient and document in detail why the patient is not expected to be medically ready for discharge on post-operative day one.
This must be a case-by-case decision based on the factors associated with the individual patient. This cannot be a blanket assessment for all patients.
When Outpatient Status Is More Appropriate
If the patient is in relatively decent health, takes no or few routine medications, or is expected to discharge on the day of the procedure, enter a status order for outpatient care. If complications arise during the procedure or recovery period, change the status to outpatient with observation services. If the patient’s clinical condition or post-operative care needs will not allow discharge on post-operative day one, change the status to inpatient.
Key Documentation Takeaway
The central lesson is that status determinations after removal from the Inpatient Only List must remain individualized, clinically justified, and thoroughly documented. The record should explain not only the diagnosis or risk factor, but also why that factor creates a reasonable expectation for at least two midnights of hospital-level care, why discharge home is not safe, when applicable, and what ongoing hospital services are required. Clear daily documentation is especially important when SNF placement is anticipated, because Medicare does not cover SNF transfer for custodial needs alone.

Strengthening Oversight of Accrediting Organizations
One observation has become increasingly difficult to ignore: I can often identify a hospital’s AO before anyone tells me, simply by observing operational workflows.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
The Centers for Medicare & Medicaid Services (CMS) recently finalized changes to strengthen its oversight of Accrediting Organizations (AOs), reaffirming that organizations granted deeming authority must consistently evaluate hospitals’ adherence to the Medicare Conditions of Participation (CoPs).
While the announcement may initially appear to be directed solely toward AOs, I believe that its implications extend much further. For hospitals, this rule represents an opportunity to reexamine how regulatory compliance is interpreted, operationalized, and ultimately measured across the healthcare industry. It is not uncommon that I witness variations among hospital organizations that focus more on accreditation behaviors from the AO and their provided standards, rather than a clear understanding and adherence to the actual CoPs.
AOs serve a critical role within the Medicare program. The CMS recent rule reinforces that this responsibility is a public trust, and emphasizes the need for increased oversight and more consistent survey performance among AOs. The intent seems straightforward in that hospitals participating in Medicare should be evaluated against the same federal requirements, regardless of which AO conducts the survey.
As someone who spends much of my time conducting operational assessments in hospitals throughout the country, I welcomed this announcement. Over the years, I have had the opportunity to work alongside organizations accredited by the two major national accrediting bodies. One observation has become increasingly difficult to ignore: I can often identify a hospital’s AO before anyone tells me, simply by observing operational workflows.
For example, I observe how the utilization management (UM) plan recognizes medical necessity, and how Important Messages from Medicare (IMMs), Medicare Outpatient Observation Notices (MOONs), and other required beneficiary notices are delivered and tracked. I evaluate utilization review committee operations, physician advisor engagement, documentation expectations, and compliance monitoring.
Very quickly, patterns begin to emerge. Some organizations devote tremendous effort toward one aspect of compliance while giving comparatively little attention to another equally important Medicare requirement. Other hospitals demonstrate exceptional operational rigor in areas that receive relatively little emphasis during surveys performed by another AO.
This variation is understandable, to a point. AOs have historically developed different educational materials, survey methodologies, and operational expectations. However, hospitals participating in Medicare are all ultimately responsible for complying with the same federal regulations.
The CoPs do not change because a hospital selected one AO instead of another. To be clear, this is not intended as criticism of any individual AO.
Each has invested tremendous effort into improving quality, patient safety, and regulatory compliance. However, the practical reality is that hospitals often adapt their compliance programs to align with what surveyors consistently evaluate, as well as from prior citations they have received.
When certain regulatory requirements receive more emphasis during one type of survey than another, organizations naturally devote additional education, auditing, and operational resources toward those areas. Over time, this can create meaningful differences in how hospitals implement mechanisms to adhere to identical federal regulations.
These operational differences should prompt an important question: are hospitals responding primarily to federal regulations, or are they responding to the survey emphasis they have historically experienced? Ideally, hospitals accredited by different organizations should demonstrate fundamentally similar compliance with these requirements, because they are ultimately being measured against the same federal expectations.
Organizations should be building sustainable compliance programs grounded directly in the CoPs and then supported by the interpretive guidelines. CMS’s strengthened oversight of AOs has the potential to move the industry closer to that goal.

Reengineering the Utilization Management Model: Part II of a Two-Part Series
An adaptive UR model organizes staff according to the work being performed, rather than the physical location of the patient.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
In Part I of this series, we explored why the traditional utilization management (UM) model is no longer sufficient to meet today’s regulatory and operational healthcare demands. The proposed removal of the Medicare Inpatient-Only (IPO) List, continued expansion of Medicare Advantage (MA), and increasing payer scrutiny have shifted the UM process from a retrospective review function to one that must proactively support level-of-care decisions and denials prevention.
Typically, hospital UM programs assign utilization review (UR) specialists by nursing unit or service line, creating workflows in which clinicians spend much of their day moving from one patient to the next based solely on location, operating off a patient list. While this model is familiar and operationally comfortable, it often obscures the actual work requiring attention at any given time. It also assumes that every hospitalized patient requires the same level of UR intervention each day, which is rarely the case.
An adaptive UR model organizes staff according to the work being performed, rather than the physical location of the patient. Specialized teams focus on distinct operational responsibilities, such as pre-admission surgical review, emergency department and direct admission reviews, observation management, concurrent inpatient reviews, and post-discharge prebill denial and authorization reconciliation. Each function requires different clinical expertise, review cadence, and workflow priorities, allowing staff to develop greater proficiency while creating standardized processes across the organization.
One area where this redesign becomes particularly valuable is the surgical population. As reliance on the IPO List diminishes, UR will need to start shifting toward evaluating patients with significant medical complexity before surgery occurs, not just immediately after. A dedicated preoperative work queue, reviewed approximately two weeks before scheduled procedures, allows UR specialists to identify patients who may require inpatient hospitalization based on clinical factors, rather than procedure alone. Early collaboration with surgeons, physician advisors, and scheduling staff supports more accurate patient status decisions, timely MA authorizations, and stronger clinical documentation – before the patient ever enters the operating room.
Observation management represents another opportunity for specialization. Observation patients often require a much higher level of monitoring than traditional inpatients, because progression-of-care needs and conversion decisions frequently occur within hours. Assigning dedicated staff to observation services creates a simulation of an observation unit without having to necessarily co-locate patients in the hospital. This works well, especially for hospitals where it is physically impossible to create a dedicated observation unit. Historically, observation workflows have focused heavily on identifying patients approaching the second midnight to determine whether inpatient conversion is appropriate. However, this represents only one component of observation management. Dedicated observation specialists can proactively address progression-of-care barriers, reduce unnecessary delays, help facilitate timely discharges, and improve patient throughput. This team is also well-positioned to oversee extended recovery patients and other outpatient-in-a-bed (OPIB) populations, creating consistency across bedded outpatient services.
Emergency department UR similarly benefits from a specialized approach. Evaluating patients at the point of entry allows medical necessity concerns, physician advisor consultations, and level-of-care determinations to occur before avoidable denials develop. Traditional models often delay these reviews, because staff believe that insufficient clinical information exists early in the encounter. However, advances in clinical decision support, artificial intelligence (AI), and real-time electronic documentation have made earlier intervention both practical and beneficial. Today’s UR specialist is no longer simply applying medical necessity criteria; they are serving as a real-time clinical resource, educating providers, collaborating with emergency physicians, and supporting accurate admission decisions before patient status becomes difficult to correct.
Building an adaptive model requires organizations to reconsider who performs the work. UR specialists should spend the majority of their time applying their clinical expertise, collaborating with physicians, physician advisors, and addressing complex medical necessity issues. Many administrative activities, such as authorization tracking, payer portal updates, fax management, scheduling peer-to-peer discussions, and post-discharge authorization reconciliation can often be delegated to trained UR technicians or other non-licensed professionals. This top-of-license approach allows the seasoned clinicians to focus on activities that require professional expertise while improving overall operational efficiency.
Technology serves as the foundation that connects these specialized workflows. Electronic medical records (EMRs) and UR technology are quickly replacing manual tracking spreadsheets with automated work queues and methods for prioritization that identify patients requiring review, notify physician advisors of escalation requests, monitor pending authorizations, and alert staff when status changes or payer requirements require action. Rather than relying on emails or secure chats, UR teams can build transparent electronic workflows for which each step of the review process is visible to case management, revenue cycle, clinical documentation integrity (CDI), and physician advisors. This level of visibility not only improves communication, but also creates valuable operational data that organizations can use to identify trends in denials, authorization delays, outpatient and observation utilization, physician advisor interventions, and throughput opportunities.
Healthcare delivery continues to evolve rapidly, and UM programs must be designed to evolve alongside it. Staffing models should reflect review demand, rather than traditional Monday-through-Friday schedules; incorporate remote and hybrid work environments, where appropriate; and adjust productivity expectations based on the complexity of each review function, rather than applying a single productivity standard across all roles. Success should be measured by meaningful outcomes such as reduced denials, improved authorization performance, shorter observation and bedded outpatient stays, cleaner claims, and stronger physician engagement.

Why the Traditional UR Model No Longer Works: Part I
Although this model has served organizations for years, today’s technology environment has fundamentally changed the role and expectations of utilization management.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
In many hospitals, utilization review (UR) still operates much as it did 20 years ago. Reviews often begin only after a patient has been admitted or a procedure has been completed. Nurses are assigned by unit, physician advisors are consulted primarily for status conversions or peer-to-peer reviews, and much of the work is tracked through spreadsheets, emails, and manual lists.
Although this model has served organizations for years, today’s technology environment has fundamentally changed the role and expectations of utilization management.
The phased removal of the Medicare Inpatient-Only (IPO) List, continued growth of Medicare Advantage (MA), and increasing payer scrutiny have exposed the limitations of a reactive UR model. Rather than asking whether a patient met criteria after admission, organizations now must identify the appropriate level of care earlier in the patient’s journey and actively support their physicians, who are documenting the clinical rationale for those decisions.
This shift requires UR to evolve, not just from a compliance standpoint, but also into an operational strategy that simultaneously supports patient progression, physician decision-making, and revenue integrity.
While medical necessity criteria remain an essential component of the review process, they should not be viewed as the endpoint of utilization management. As technology continues to advance to support increased scale and UR production, professionals should start considering how their position is going to shift – and reevaluate what requires a nurse to fill a supportive role for items such as sending clinicals and inputting payer responses.
For top-of-license performance, the role of the UR specialist will be moving to evaluate and support the information that may be part of the patient’s record, but was not captured in the patient’s provider documentation. This subtle but important shift transforms UR from an auditing function, checking the boxes for “met” and “unmet” reviews, into a collaborative clinical partner that works alongside providers, clinical documentation integrity (CDI), case management, and physician advisement to improve documentation, ensure the appropriate level of care, and prevent avoidable denials before claims are submitted.
Many organizations continue to rely on disconnected spreadsheets, email communication, and manual tracking processes that create unnecessary rework and limit visibility into the UR process. These fragmented workflows make it difficult to measure physician advisor involvement, identify authorization delays/denials, or provide meaningful operational feedback across clinical and revenue cycle teams.
Technology vendors, electronic medical record (EMR) workflows, and work queues allow organizations to automate referrals, monitor medical necessity milestones, and create transparent communication – and tell a data story across the continuum of the clinical and revenue cycle. Thus, the ideal UR specialist is not necessarily the seasoned nurse, but someone with effective communication and technology skills.
Healthcare has reached a pivotal moment wherein UR can no longer function solely as a retrospective review mechanism. By shifting interventions earlier, strengthening physician collaboration, and focusing on operational efficiency, rather than status correction, hospitals can improve compliance, reduce denials, and better support both patients and providers.

Physician Advisors: Leaders, Champions, Educators
Under essentially every circumstance, physician advisors are most effective when working in lockstep with their partners in case and utilization management leadership.
By Juliet Ugarte Hopkins, MD, ACPA-C
Physician advisors should be involved in far more than secondary status reviews and peer-to-peer calls. They must stand out as leaders, resources, and champions of their case and utilization management teams, and be recognized as educators and problem-solvers for their hospitals’ medical staff. If you’re a physician advisor and this doesn’t sound like your role, or if you work with a physician advisor, but this description is way beyond their professional line of sight, it might be time to reconsider the position’s goals and requirements.
There are many iterations, facets, and ranges of scope involving the physician advisor role within hospital settings. But one thing should be clear: when addressing escalations from case or utilization managers about real-time patient status, physician advisors must understand the Medicare Two-Midnight Rule inside and out. This includes the exceptions, how MCG or InterQual criteria fit in, and a firm understanding of the Centers for Medicare & Medicaid Services (CMS) definition of “medically necessary hospital care.” Physician advisors should be their hospital’s expert and trusted resource about the Rule, ready to answer questions from anyone within any department in the hospital or health system.
This knowledge should not be kept to themselves. It is imperative for physician advisors to educate their admitting clinicians about the Rule. Why? Because of the Code of Federal Regulations, Title 42, Chapter IV, Subchapter B, Part 412, Subpart A, 412.3: “…an individual is considered an inpatient of a hospital, including a critical access hospital, if formally admitted as an inpatient pursuant to an order for inpatient admission by a physician or other qualified practitioner…the order must be furnished by a qualified and licensed practitioner who has admitting privileges at the hospital…who is knowledgeable about the patient’s hospital course, medical plan of care, and current condition. The practitioner may not delegate the decision (order) to another individual who is not authorized by the State to admit patients, or has not been granted admitting privileges applicable to that patient by the hospital’s medical staff.”
The Code is very clear: clinicians are required to understand the Medicare Two-Midnight Rule and appropriately assign their patients to inpatient or outpatient status with observation services. True, this status-determining modality won’t be appropriate for everyone – for example, patients covered by commercial plans – but it will compliantly capture those covered by Medicare.
What about utilization or case managers? Shouldn’t they assist with status determination efforts by providing guidance to clinicians when needed? Absolutely – which is why physician advisors should also ensure that they educate these teams. The goal is not for the utilization managers to direct the status decision to the clinicians and expect a blind co-sign of an inpatient status or observation service order. They should serve as an extension of the physician advisor when working with medical staff, enforcing and amplifying their knowledge about the Medicare Two-Midnight Rule and medical necessity. Only after a physician advisor has comprehensively and routinely provided education to utilization managers and clinicians alike can the two teams work collaboratively to assign appropriate patient status at the time of hospitalization, and in the following 24-48 hours.
While they may not remember or even be aware of everything pertinent from a utilization and case management standpoint, when it comes to CMS rules and regulations, physician advisors should be well-versed in how to find the answers, when asked. Additionally, they should understand how specific processes they are involved with relate to the Conditions of Participation, conditions for coverage, and so on.
If something is going awry within case or utilization management, if a step is missing within a CMS-mandated process, or if it’s discovered that there is misunderstanding about a concept within a specific group or involving a single individual, physician advisors should be all over it.
No, they cannot boil the ocean or right every wrong. But as leaders, experts, educators, and collaborators, they should persistently strive to offer solutions or make corrections. Under essentially every circumstance, physician advisors are most effective when working in lockstep with their partners in case and utilization management leadership.
Like the partnership with medical staff, persistent and routine communication and collaboration is a must.
Even if “only” participating in their hospital’s peer-to-peer process, there is much to gain here as well, if a physician advisor is truly invested. Is the initial denials assessment process as efficient as it should be? Are the qualifiers directing the decision of which cases are escalated to peer-to-peer versus which are re-billed as observation, producing favorable results? Track and assess outcomes on a routine basis, and consider how statusing efforts might be influencing the trends.
If there’s an opportunity for improvement or conflicting concepts leading to suboptimal results, the physician advisor should take the lead on brainstorming a corrective or alternative course of action with their utilization, denials, and even medical-staff partners.
Physician advisors are team captains and should demonstrate passion and dedication for their role, thriving when collaborating with all members of the hospital’s care and administrative teams.

Are You Sick Enough? A Look at New Medicaid Work Requirements
Healthcare organizations are already facing increasing administrative responsibilities; the addition of Medicaid work requirement exemptions introduces another layer of documentation and additional risk of administrative burnout.
By Tiffany Ferguson, LMSW, CMAC, ACM, FCM
The Centers for Medicare & Medicaid Services (CMS) recently issued an Interim Final Rule with Comment (CMS-2454-IFC) implementing the Medicaid Community Engagement Requirement established under Public Law 119-21, referred to by CMS as the Working Families Tax Cut (WFTC) legislation. Beginning no later than Jan. 1, 2027, certain adults ages 19 through 64 will be required to complete at least 80 hours per month of qualifying activities, including employment, education, job training, or community service, as a condition of Medicaid eligibility.
While much of the public discussion surrounding Medicaid work requirements has focused on employment, the more significant operational questions may center on implementation, verification, and access to care. For healthcare organizations, the issue is less about whether beneficiaries should work and more about how states and providers will determine eligibility for work.
The rule applies to non-pregnant adults between the ages of 19 and 64 who are not entitled to Medicare and receive coverage through Medicaid expansion populations or certain Section 1115 demonstrations.
Individuals may satisfy the requirement through multiple pathways. In addition to qualifying activities, beneficiaries may demonstrate compliance through earnings equal to at least 80 times the federal minimum wage, which equates to approximately $580 per month in 2026. Activities may be combined to meet the monthly threshold. States are required to verify compliance with application and renewal. If compliance cannot be verified, states must provide notice and allow beneficiaries 30 calendar days to demonstrate compliance or establish that they qualify for an exemption before denying or terminating coverage. Failure to do so may result in disenrollment, although individuals may reapply at any time.
At initial application, states may require individuals to demonstrate compliance during one to three months preceding enrollment. At renewal, beneficiaries must show compliance for one or more months during the prior eligibility period. These lookback periods introduce an entirely new layer of eligibility complexity.
Who is Exempt?
Congress excluded several populations from the requirement, including pregnant and postpartum individuals, indigenous peoples, certain caregivers, individuals already satisfying Supplemental Nutrition Assistance Program (SNAP) or Temporary Assistance for Needy Families (TANF) requirements, and persons considered medically frail. States may also grant temporary hardship exceptions for individuals receiving inpatient hospital services, traveling for specialized medical care, residing in areas experiencing nationally declared disasters, or living in counties with high unemployment.
Who Determines Medical Frailty?
Perhaps the most important question raised by the rule is not who must work, but who determines when someone is unable to.
The Interim Final Rule requires states to use all available reliable information, including adjudicated claims and encounter data from the previous 12 months, before requesting additional information from beneficiaries. States must verify not only that a diagnosis exists, but that the condition significantly impairs the individual’s ability to comply with the community engagement requirement. Beginning Jan. 1, 2028, self-attestation for medical frailty may generally be used only once, when claims data are unavailable. Subsequent determinations may require additional documentation. This distinction is critical.
According to the ruling, possessing a diagnosis alone does not automatically establish medical frailty. The rule requires evidence that the condition meaningfully limits the person’s ability to meet the requirement. Consequently, physicians and other clinicians may increasingly be asked to certify not simply the presence of cancer, chronic pain, depression, substance use disorders, or cognitive impairment, but the functional consequences associated with those conditions. This would likely be similar to disability determinations and Family and Medical Leave Act (FMLA) certifications, wherein providers may find themselves completing forms, supplying medical records, and responding to requests from state agencies.
Healthcare organizations are already facing increasing administrative responsibilities; the addition of Medicaid work requirement exemptions introduces another layer of documentation and additional risk of administrative burnout.
Providers may be asked to certify medical frailty or functional limitations, verify temporary inability to work following hospitalization, respond to state requests for information, and/or participate in appeals processes when eligibility is denied. These responsibilities are unlikely to generate reimbursement and may disproportionately affect safety-net hospitals, rural providers, and organizations serving large Medicaid populations.
Access to Care Concerns
Although CMS has committed approximately $200 million in grants and announced more than $600 million in private-sector technology support to assist implementation, this is going to be a significant lift to operationalize. Perhaps the greatest concern associated with work requirements is not whether beneficiaries are employed, but whether otherwise eligible individuals may lose coverage because of administrative complexity.
Past experiences with Medicaid work requirements demonstrated that coverage losses often occurred because individuals could not navigate reporting requirements, not because they failed to satisfy them. Individuals with behavioral health conditions, unstable housing, low health literacy, transportation challenges, or limited access to technology may encounter difficulties complying with complex documentation requirements, even when they qualify for exemptions.
Coverage interruptions may result in delayed care, medication nonadherence, increased emergency department utilization, avoidable hospitalizations, and rising rates of uncompensated care for providers.
CMS views the Community Engagement Requirement as a pathway toward economic independence and poverty reduction. Whether these goals are achieved will depend not only on employment opportunities, but also on how effectively states and healthcare systems operationalize the requirements without creating unintended barriers to care.

Case Management Corner: Improving Post-Partum Discharge Outcomes
Maternal health issues are common in the weeks and months after birth, and can affect a child’s short and long-term trajectory.
By Kelly Bilodeau
When a new mother leaves the hospital, it doesn’t just mark the end of a hospital stay; it’s the beginning of a complex, decades-long relationship.
Recovery from childbirth often occurs alongside around-the-clock care for an infant, and many variables affect the success of the transition, including the physical and mental health of the mother, the support structure at home, and the temperament and health of the baby. This means that there’s really no such thing as a routine discharge after childbirth, said Kalie Wolfinger, LCSW, manager of clinical services at Phoenix Medical Management.
The transition home also marks a crucial window when case managers and social workers can intervene to improve outcomes in mother and baby pairs. But doing so may require additional training and a rethinking of traditional discharge procedures, Wolfinger said.
Traditional hospital discharges prioritize checklists and narrow safety-based education on topics such as safe sleep strategies and car seat safety. But they often don’t focus on other critical strategies such as up-close patient mental health assessments, promoting bonding and attachment, and looking for signs of past trauma that may hinder healthy parenting, Wolfinger said.
Maternal challenges linked to poorer outcomes
Maternal health issues are common in the weeks and months after birth, and can affect a child’s short- and long-term trajectory. As many as 20% of women who have given birth experience symptoms of postpartum depression, according to Brown University Health, and rates of the disorder have doubled over the last decade, according to a JAMA analysis. It’s not just an issue that affects the mother. One 2025 study found that infants whose mothers experienced postpartum depression had double the risk for developmental delays during the first year.
Other common issues that social workers and case managers should screen for include:
Maternal anxiety
Substance use disorders
Intimate partner violence
Social determinants of health (e.g. poverty, housing insecurity)
Social workers and case managers can assess patients for these risk factors using a trauma-informed and culturally sensitive approach. Observation helps gauge maternal-infant bonding and interactions.
Building infrastructure for better transitions
Providing this type of critical assistance to mothers goes beyond traditional discharge planning. It’s not just about ensuring equipment is ordered, prescriptions are filled, and follow-up visits are scheduled, but about creating bridges for patients to access outpatient services and early intervention, Wolfinger said.
It’s not always easy to create these ties, because structural barriers often get in the way. Hospital systems often don’t support this type of work and community resources may be fragmented, she said.
Social workers and case managers can also encounter thorny legal issues. It’s a delicate balance to prioritize maternal rights while safeguarding infant wellbeing. Hospitals often have standardized protocols and risk management guidelines to reduce the potential for errors and protect against potential liability, but trained professionals also need to be able to rely on their own gut instincts during patient interactions, Wolfinger said.
Mothers may also have a disincentive to share concerns about their mental health or substance use disorders with caregivers, fearing that doing so may trigger mandatory reporting requirements or intervention from child protective services.
Specialized training can equip professionals with the tools they need to navigate these issues, ensuring better support for at-risk mother and child pairs. “Getting it wrong can have long-term consequences,” Wolfinger said. “But getting it right can have a major impact on both mom and baby over time.”
Case Management Corner is your go-to source for insightful discussions on relevant topics in case management. Through an engaging interview-style format, our team members share their expertise, experiences, and best practices to keep you informed and empowered. Whether you're looking for industry updates, practical strategies, or real-world perspectives, we bring you valuable conversations designed to enhance your knowledge and support your professional growth. Stay tuned for expert insights straight from the field! Kelly Bilodeau has been a longtime writer for HCPro’s Case Management Monthly.

Centralized Post-Acute Authorization: Improving Efficiency, Reducing Administrative Burden
While these tasks are essential to patient progression, they are highly administrative and often divert professional staff from more complex clinical and discharge planning responsibilities.
By Marie Stinebuck, MBA, MSN, ACM
As healthcare organizations face increasing pressure to improve efficiency and reduce administrative burden, many are reevaluating how post-acute care authorizations are managed. Traditionally, nurse case managers and social workers have spent significant time gathering clinical documentation, navigating payer websites, and communicating with insurance companies to secure authorization for skilled nursing facilities, inpatient rehabilitation facilities, long-term acute care hospitals, and home health services. While these tasks are essential to patient progression, they are highly administrative and often divert professional staff from more complex clinical and discharge planning responsibilities.
A centralized post-acute resource center (PARC) authorization process offers an effective solution. By consolidating post-acute authorization activities into a dedicated workflow supported by specialized staff, hospitals can streamline operations, reduce delays, and allow case managers and social workers to focus on patient-centered interventions. In this model, the PARC team may consist of authorization coordinators, case management assistants, or utilization review technicians who assume responsibility for obtaining post-acute authorizations.
These team members are trained to access payer portals, upload clinical documentation, complete required forms, and monitor authorization status. Because many payers now offer online portals with standardized submission tools, much of the work can be completed electronically without lengthy phone calls or fax transmissions. Use of these portals also decreases manual processes and helps prevent errors associated with manual workflows. In the case of a denial, the PARC team can support appeals and resubmission of clinical documentation for a lower level of care, as needed.
It is vital to create standardized work related to portal use for training and education. The PARC team will likely use multiple payer portals, each with unique guidelines and processes for managing authorization requests. Key elements to include in standardized work include the regional contact person for each portal, instructions for obtaining access for new users, and support line contacts for troubleshooting issues that may arise.
The centralized process begins when the case manager or social worker identifies the appropriate post-acute level of care and confirms the patient’s discharge plan. Once the receiving facility is selected and confirms its ability to accept the patient, the case management team provides the necessary clinical summary and anticipated discharge details to the authorization support team. From there, the support staff manage the end-to-end authorization process, including submission, follow-up, and communication of approval information to the care team and receiving provider.
Using payer portals significantly reduces manual work. Clinical documentation can be uploaded directly from the electronic medical record, templates can standardize submissions, and dashboards allow staff to track pending requests in real time. This approach minimizes duplicate data entry, decreases errors, and creates greater transparency into authorization turnaround times. Organizations can also develop work queues to prioritize urgent discharges and assign tasks based on workload.
Centralization delivers several important benefits. First, it improves efficiency by allowing a smaller group of trained staff to develop expertise in payer-specific requirements. Second, it reduces discharge delays caused by missed submissions or inconsistent follow-up. Third, it enhances staff satisfaction by removing administrative tasks from nurses and social workers, enabling them to devote more time to clinical assessments, family discussions, and care coordination.
Ultimately, a centralized PARC team can support both operational and clinical goals. By leveraging payer portals and assigning administrative tasks to support staff, healthcare organizations can reduce unnecessary manual work, accelerate discharges, and maximize the value of professional case management resources.

Case Management Corner: Use Your EMR To Revamp UR Communication
Improving communication with these tools will do more than just streamline processes. It can help build bridges between bedside care, hospital operations, and the billing department.
By Kelly Bilodeau
Healthcare is rapidly evolving, but utilization management (UM) still often relies on outdated communication and documentation strategies, such as emails and faxes based on unit-based assignments and static patient lists. These outmoded exchanges struggle to keep pace with the demands of the modern revenue cycle.
It’s time for a change, and luckily, the needed transformation is not one that requires high-cost new technology, just smarter use of your facility’s existing electronic medical record (EMR).
“Most hospitals already possess the technology needed to transform their UM programs; they simply need to reimagine how those tools are used,” said Sara Williams, vice president of clinical strategy at Phoenix Medical Management.
Repurposing existing tools
It’s possible to transform UR by reapplying existing EMR tools, such as reporting systems and communication platforms, to make the necessary shift toward proactive, connected workflows, she said.
Improving communication with these tools will do more than just streamline processes. It can help build bridges between bedside care, hospital operations, and the billing department. Using the EMR can also help ensure that the physician advisor’s clinical judgment, correct payer terminology, and verification of medical-necessity criteria are captured in the patient’s medical record. This is not always possible using legacy tools such as spreadsheets or anecdotal documentation, Williams said.
“Physician Advisors and UR nurses must be equipped with tools that allow their work to be visible, measurable, and aligned with organizational outcomes,” she said.
EMR systems can ensure continuity and follow-through by formalizing the documentation process using EMR-integrated UR tools and interactive dashboards. This allows UR nurses and physician advisors to easily communicate to build a clinical record that will withstand payer scrutiny and draw a straight line from patient admission to final claim resolution.
Providing support for a new model
However, like any technological leap, this change requires human support. Organizations need to ensure that UR team members are still engaged and collaborating with one another, particularly as more work is done outside the hospital.
Collaborating closely with the analysts who support your EMR is a key first step in transitioning documentation and workflows from spreadsheets and external resources into integrated EMR tools. These analysts have access to the latest available system capabilities and can help incorporate those features into your existing workflows to optimize documentation, streamline communication within the system, and enhance both reporting and overall documentation efficiency.
Working remotely has advantages, but it also carries risks, Williams said. With this in mind, organizations should develop tools and training to ensure that physician advisors and UR nurses can carry out concurrent reviews, work together effectively, and understand and meet payer-specific requirements, Williams said.
“Done right, the digital tools provided by the EMR can help Physician Advisors and UR leaders to optimize performance and advance organizational excellence.”
Case Management Corner is your go-to source for insightful discussions on relevant topics in case management. Through an engaging interview-style format, our team members share their expertise, experiences, and best practices to keep you informed and empowered. Whether you're looking for industry updates, practical strategies, or real-world perspectives, we bring you valuable conversations designed to enhance your knowledge and support your professional growth. Stay tuned for expert insights straight from the field! Kelly Bilodeau has been a longtime writer for HCPro’s Case Management Monthly.